Research Article | | Peer-Reviewed

Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal

Received: 20 April 2025     Accepted: 6 May 2025     Published: 18 June 2025
Views:       Downloads:
Abstract

Mental health among students in Senegal remains an under-explored area, with limited research and prevention efforts. At the African Center for Higher Studies in Management (CESAG), students face high academic demands, highlighting the importance of investigating stress, anxiety, and depression within this population. This study aimed to identify factors associated with anxiety-depressive states, specifically stress, anxiety and depression, among CESAG students. A cross-sectional, observational, descriptive, and analytical study was conducted from July 22 to August 23, 2024. Data were collected through an electronic questionnaire. Stress, anxiety, and depression were assessed using the Perceived Stress Scale (PSS), the Generalized Anxiety Disorder-7 (GAD-7) score, and the Patient Health Questionnaire-9 (PHQ-9) score, respectively. Data analysis was performed using RStudio (version 2024.12.1.563). Informed and voluntary consent of the participants was ensured. A total of 426 students completed the online questionnaire. The mean age was 23.4 years. Stress was observed in 45.6% of students, anxiety in 21.4%, and depression in 35.4%. Risk factors for stress included belonging to the [20-25 years[ age group (ORa = 5.68, 95%CI [1.67-19.31]) or the ≥30 years group (ORa = 8.8, 95%CI [1.5-51.64]), poor sleep quality (ORa = 7.05, 95%CI [2.32-21.44]), low financial income (ORa = 11.23, 95%CI [4.34-29.06]), low self-esteem (ORa = 15.13, 95%CI [3.18-72.13]) or moderate self-esteem (ORa = 7.96, 95%CI [2.83-22.4]), a negative emotional state (ORa = 4.7, 95%CI [1.64-13.46]), and the absence of physical activity (ORa = 5.03, 95%CI [1.88-13.49]). Living alone was a protective factor against anxiety among students (ORa = 0.16, 95%CI [0.09-0.29]). Depression was associated with several risk factors: poor sleep quality (ORa = 8.07, 95%CI [2.72-23.88]), low financial income (ORa = 4.38, 95%CI [1.42-13.48]), living alone (ORa = 3.53, 95%CI [1.1-11.34]), poor diet (ORa = 13.03, 95%CI [3.84-44.18]), low self-esteem (ORa = 18.21; 95%CI [2.62-126.41]) or moderate self-esteem (ORa = 9.19, 95%CI [1.66-51.01]), and a negative emotional state (ORa = 5.54, 95%CI [1.64-18.71]). A passive coping style was found to be protective (ORa = 0.25, 95%CI [0.08-0.8]). These findings emphasize the importance of preventive strategies to promote CESAG students’ mental health and well-being. Targeted awareness campaigns and psychological support are essential to achieving this goal.

Published in Central African Journal of Public Health (Volume 11, Issue 3)
DOI 10.11648/j.cajph.20251103.13
Page(s) 113-134
Creative Commons

This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.

Copyright

Copyright © The Author(s), 2025. Published by Science Publishing Group

Keywords

Stress, Anxiety, Depression, PSS, GAD-7, PHQ-9

1. Introduction
Anxiety-depressive states are mental health conditions characterized by persistent emotional distress, cognitive dysfunction, and reduced ability to cope with daily demands. They include stress, anxiety, and depression as core components. Stress refers to the consequence of an organism’s inability to adequately respond to mental, emotional, or physical demands. Anxiety is characterized by intense feelings of fear, accompanied by somatic symptoms indicating an overactive autonomic nervous system. Depression manifests as a loss of interest or pleasure, sadness, feelings of guilt or low self-esteem, disrupted sleep or appetite, extreme fatigue, and poor concentration . A mentally healthy student is one who thinks clearly and logically, is able to initiate appropriate social relationships, and is eager to learn with a substantial ambition to implement their future plans .
Previous studies have shown that stress negatively affects students’ physical and cognitive abilities . When associated with anxiety and depression, occupational stress as experienced by students can influence their quality of life and decrease academic performance due to impaired cognitive functioning induced by anxiety, such as memory disturbances, mental blockages, difficulty making decisions, and increased sensitivity to others’ evaluations. Similarly, high levels of stress, anxiety, and depression can lead to poor quality of life, substance abuse, and suicide .
Globally, the incidence of stress, anxiety, and depression among students is increasingly reported . Studies have indicated that over 85% of students report feeling overwhelmed by the growing demands of academic programs. This is further compounded by high levels of precariousness and family separation, as young adults often have to live in large cities to pursue their education. Most students must quickly gain independence, learn to manage their finances, and balance and increased academic workload with social activities. Choices regarding specialized programs, the search for internships, and the management of administrative tasks related to their career choices can also generate significant anxiety. These external pressures can lead to increased anxiety, loneliness, depression, sleep disturbances, and even suicidal thoughts .
In Senegal, as in most sub-Saharan African countries, mental health remains a poorly explored field of research and action . Research in this area is described as “rare, fragmented, and ineffective” In the country, mental health is influenced by various mystical-religious interpretations . The promotion and prevention of mental health and well-being among adolescents and young people is not a priority in the existing mental health services. The Department of Mental Health (DSM) of the Ministry of Health and Social Action (MSAS) highlights the gap between the resources available and the objectives to be achieved in order to ensure better mental health for groups identified as most vulnerable
The African Center for Higher Studies in Management, known as CESAG , is an international public institution based in Dakar (Senegal), specializing in training, consulting, and research in economics and management sciences. A prestigious and excellent institution under the supervision of the Central Bank of West African States (BCEAO), it trains students from sub-Saharan Africa, who are held to a high level of academic rigor. Generating data on mental health and well-being issues within this population is a significant contribution to the field of research in Senegal and sub-Saharan Africa. This contribution is all the more noteworthy as it concerns a priority target group for mental health and well-being: a young, student population facing real academic and social pressures.
Thus, our research was justified by the importance of exploring stress, anxiety, and depression among CESAG students, with the aim of contributing to the enhancement of knowledge on mental health in demanding academic environments. The findings of this study could provide insights for targeted interventions aimed at improving students’ well-being and fostering an educational environment conductive to their personal development within the institution.
2. Materials and Methods
This was a cross-sectional, observational, descriptive, and analytical study conducted from July 22 to August 23, 2024. The study population consisted of all students officially enrolled at CESAG during the 2023-2024 academic year. Inclusion criteria required that participants had access to a digital device for the online self-administration of the data collection tool. Excluded from the study were ten students who were recruited to assist the principal investigator in raising awareness in the classrooms selected for the sample. The sample size was calculated using Schwartz’s formula (N=384), adjusted for the cluster effect (N=576), and further increased by 5% to account for non-respondents, resulting in a final target sample size of 605 students.
The sample was selected using a two-stage cluster sampling method. In the first stage, a comprehensive list of 70 classes was established, followed by a simple random selection with cumulative enrollment. The threshold of 605 students was reached upon selecting the 23rd class. In the second stage, all students from the randomly selected classes were included exhaustively.
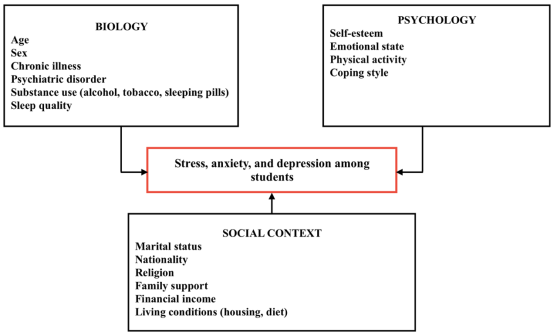
The variables of interest were assessed using self-administered tools: the Perceived Stress Scale (PSS) for stress , the Generalized Anxiety Disorder-7 (GAD-7) score for anxiety , and the Patient Health Questionnaire-9 (PHQ-9) score for depression . Explanatory variables related to biological, psychological, and social context determinants were collected in accordance with the study’s conceptual framework, based on the biopsychosocial health model (G. Engel, 1977). Figure 1 presents the conceptual framework of the study.
Figure 1. Conceptual framework of the study, based on G. Engel’s biopsychosocial model.
The PSS assesses the perception of stress in daily life through ten items. The questions measure how frequently life situations were perceived as stressful over the past month. Each item is scored from 0 (never) to 4 (very often), with a maximum total score of 40 points. The interpretation of the results is as follows: 0-13: low stress; 14-26: moderate stress; 27-40: high stress.
The GAD-7 score assesses the severity of anxiety disorders using seven items. The questions focus on anxiety symptoms experienced over the past two weeks. Each item is scored from 0 (not at all) to 3 (nearly every day), with a total score ranging from 0 to 21 points. The interpretation of the results is as follows: 0-4: minimal anxiety; 5-9: mild anxiety; 10-14: moderate anxiety; 15-21: severe anxiety.
The PHQ-9 score assesses depression using nine items. The questions cover depressive symptoms experienced over the past two weeks. Each item is scored from 0 (not at all) to 3 (nearly every day), with a total score ranging from 0 to 27 points. The interpretation of the results is as follows: 0-4: minimal depression; 5-9: mild depression; 10-14: moderate depression; 15-19: moderately severe depression; 20-27: severe depression.
Self-esteem was first measured using a numerical scale ranging from 1 to 10, with 1 representing the lowest level of self-esteem and 10 the highest. It was then categorized into three levels: low, moderate, and high, corresponding to the intervals [0-8], and [8-10], respectively. The thresholds were defined to capture clear distinctions in self-perception. A score below 5 indicated a predominantly negative self-view, while a score of 8 or above denoted a particularly high and confident self-regard, distinguishing it from more moderate levels of self-esteem.
The coping style was assessed through a single-choice question asking participants to select the strategy they most commonly used. The response options were based on the following typologies: problem-focused coping (actively seeking solutions to encountered problems), emotion-focused coping (distancing oneself from the problem, practicing sports or meditation), avoidance coping (ignoring or repressing the problem, using psychoactive substances to forget it), and social support-seeking (asking for help from others).
A questionnaire (annex) based on the conceptual framework, was deployed online via the KoboToolbox platform for data collection. It consisted of 30 items distributed across four chapters as follows:
1) information on the biological dimension: age, sex, medical history, substance use (tobacco, alcohol, sleeping pills), and sleep quality;
2) information on the social context: marital status, nationality, religion, family support, financial income level, and living conditions (housing and diet);
3) information on the psychological dimension: self-esteem, emotional state, physical activity, and coping style;
4) information on the variables of interest: PSS, GAD-7 score, and PHQ-9 score.
A pre-test of the questionnaire was conducted using 17 students from the Higher School of Applied Economics (ESEA), another training institution comparable to CESAG, before validating the final version. The principal investigator provided prior training to the ten recruited students who assisted in raising awareness in the selected classrooms regarding the survey aspects, before conducting the pre-test and data collection. The data collection process was conducted entirely online. The link to the final version of the questionnaire was shared with the sample students via WhatsApp. The team of ten recruited students visited the selected classrooms to announce the upcoming launch of the study and encourage the objective self-administration of the questionnaire. They were volunteers and received no financial compensation.
At the end of the data collection period, the online database was exported and cleaned using Microsoft Excel from the Office 365 suite. Data analysis was performed using RStudio (version 2024.12.1.563) . The statistical analysis involved a descriptive analysis of the biological, social, and psychological dimensions, as the variables of interest, followed by an inferential analysis, first bivariate, then multivariate.
In the descriptive analysis, the results are presented as frequency and percentage for qualitative variables, and as mean and standard deviation (SD) for quantitative variables. When relevant, the medians and extremes of the quantitative variables are also presented.
In the analytical section, the variables of interest were recoded into binary qualitative variable (yes or no). Students classified as having moderate or high stress were considered stressed, while those with low stress were considered not stressed. Students classified as having moderate or severe anxiety were considered anxious, while those with minimal or mild anxiety were considered not anxious. Students classified as having moderate, moderately severe, or severe depression were considered depressed, while those classified as having minimal or mild depression were not depressed.
Similarly, explanatory variables with more than two categories were recoded into binary variables. The categories yes, occasionally and yes, regularly were combined into a single category yes, reflecting any level of exposure or behavior, regardless of frequency. This approach was guided by public health considerations, as even occasional use may have potential health impacts. Sleep quality and diet were recoded into poor (very poor and poor) and good (average, good, and very good). This categorization aimed to distinguish unfavorable conditions from acceptable or beneficial ones in terms of general well-being. Financial income was recoded into low (very low and low) and good (average, good, and very good), allowing for the identification of economic disparities while maintaining a balanced distribution of participants across categories. Emotional state was recoded into negative (very negative and somewhat negative) and positive (neutral, somewhat positive, and very positive), based on the assumption that a neutral emotional state is closer to a positive than a negative disposition. Coping style was recoded into categories passive (distancing oneself, ignoring or repressing, using psychoactive substances in response to problems) and active (actively seeking a solution, asking for help, and practicing sports or meditation in response to problems). This recoding was based on a widely accepted conceptual distinction in psychology between passive and active coping strategies. Passive strategies involve avoidance or withdrawal behaviors, which are generally less effective in the long term. In contrast, active strategies focus on directly addressing the problem or managing stress in a healthy, constructive manner.
The bivariate analysis involved cross-tabulating the variables stress, anxiety, and depression with all other variables. The p-values were calculated in order to perform a multivariate analysis that included all variables with a p-value less than or equal to 25% from the bivariate analysis.
The multivariate analysis was performed using binary logistic regression. We used the stepwise backward method through two different approaches. The first approach involved conducting an automated stepwise backward with all variables that had a p-value less than or equal to 25% from the bivariate analysis. The second approach involved an automated stepwise backward full model with all collected variables, including those with a p-value greater than 25% from the bivariate analysis. The most parsimonious model from the two approaches was selected.
The parsimony of the models (one model for stress, one for anxiety, and one for depression) was assessed using the Akaike Information Criterion (AIC). The residuals were analyzed using graphical methods. Subjects with leverage effects (outliers) were removed to enhance the robustness of the models. Multicollinearity was checked using the Variance Inflation Factor (VIF). Interactions between variables in the selected models were examined, tested, and ultimately, the best models were retained by comparing the AICs of the models with interactions and those without. The calibration of the models was tested using the Hosmer-Lemeshow test. Model performance was assessed, including Receiver Operating Characteristic (ROC) curves and Areas Under the Curves (AUC).
The results of the analyses were extracted from RStudio, and data entry and text processing were performed using Microsoft Word.
A consent form requesting student approval was included at the beginning of the online questionnaire. No medications were administered, nor were biological fluid samples taken, nor were clinical or paraclinical examinations conducted in the study. Participation was voluntary, anonymous, and non-remunerated. However, practical psychological support advice was provided to students who needed it. The collected data were kept and processed in a strictly confidential manner.
3. Results
3.1. Descriptive Results
A total of 426 students completed the online questionnaire. The respondents had a mean age of 23.4 years (SD = 4.60) and a median age of 23.0 years (range = 17-37 years). The most represented age group was [20-25 years[ (36.8%), followed equally by those under 20 years and those aged [25-30 years[ (25.6% each). The majority of respondents were female (57.3%). A history of chronic diseases was reported by 9.4% of respondents, while no participant reported a history of psychiatric disorders. Occasional alcohol consumption was reported by 67 students (15.7%), whereas 18 students (4.2%) stated that they consumed alcohol regularly. Additionally, 7.3% of students reported occasional smoking. Sleep quality was rated as very poor and poor by 20.2% and 14.3% of students, respectively. Four students (0.9%) reported occasional use of sleeping pills, while five students (1.2%) stated they used them regularly.
The most represented nationality was Senegalese (32.1%). The majority of respondents identified as Muslim (57.5%) or Christian (40.8%). Most participants were single (91.3%). The majority of students received financial support from their families, either occasionally (26.1%) or regularly (72.3%). Financial resources were perceived as very low by 21.1% of respondents and low by 27.9%. Students living alone accounted for 21.6% of the sample, while those living in shared accommodations represented 28.2%. Diet quality was rated as very poor and poor by 18.5% and 13.6% of students, respectively.
Students most frequently reported moderate self-esteem (36.6%) or high self-esteem (36.2%), while 27.2% reported low self-esteem. A very negative emotional state was reported by 27.7% of respondents, whereas 12.4% described their emotional state as somewhat negative. Only 30.3% of respondents engaged in regular physical activity. The predominant coping style was passive (54.9%), including 23.0% who distanced themselves from problems, 18.5% who ignored or repressed them, and 13.4% who used psychoactive substances to cope. The most frequently reported active coping style was actively seeking solutions to problems (23.7%), followed by asking for help from others (11.5%). Table 1 presents the descriptive results of the biological, social, and psychological dimensions.
Table 1. Descriptive results of biological, social, and psychological dimensions (N=426).

Variables

Frequency (n)

Percentage (%)

Biological dimension

Age group

<20 years

109

25.6

[20-25 years [

157

36.8

[25-30 years [

109

25.6

≥30 years

51

12.0

Sex

Female

244

57.3

Male

182

42.7

Chronic illness

No

386

90.6

Yes

40

9.4

Psychiatric disorder: No

426

100.0

Alcohol

No

341

80.0

Yes, occasionally

67

15.7

Yes, regularly

18

4.2

Tobacco

No

395

92.7

Yes, occasionally

31

7.3

Sleeping pills

No

417

97.9

Yes, occasionally

4

0.9

Yes, regularly

5

1.2

Sleep quality

Very poor

86

20.2

Poor

61

14.3

Average

110

25.8

Good

75

17.6

Very good

94

22.1

Social dimension

Nationality

Senegalese

137

32.1

Ivorian

85

20.0

Burkinabe

58

13.6

Nigerien

54

12.7

Bissau-Guinean

47

11.0

Others

45

10.6

Religion

Islam

245

57.5

Christianity

174

40.8

Others

7

1.6

Marital status

Single

389

91.3

Married

33

7.7

Divorced

4

0.9

Family support

No

7

1.6

Yes, occasionally

111

26.1

Yes, regularly

308

72.3

Financial income

Very low

90

21.1

Low

119

27.9

Average

141

33.1

Good

65

15.3

Very good

11

2.6

Housing

Living alone

92

21.6

Shared accommodation

120

28.2

With family

214

50.2

Diet

Very poor

79

18.5

Poor

58

13.6

Average

98

23.0

Good

109

25.6

Very good

82

19.2

Psychological dimension

Self-esteem

Low

116

27.2

Moderate

156

36.6

High

154

36.2

Emotional state

Very negative

118

27.7

Somewhat negative

53

12.4

Neutral

80

18.8

Somewhat positive

113

26.5

Very positive

62

14.6

Physical activity

No

194

45.5

Yes, occasionally

103

24.2

Yes, regularly

129

30.3

Coping style

Actively seeking to solve the problem

101

23.7

Distancing oneself from the problem

98

23.0

Ignoring or repressing the problem

79

18.5

Using a psychoactive substance to forget

57

13.4

Asking for help from others

49

11.5

Practicing sports or meditation

42

9.9

Age*: mean (SD) = 23.4 (4.60); median [minimum, maximum] = 23.0 [17.0, 37.0]
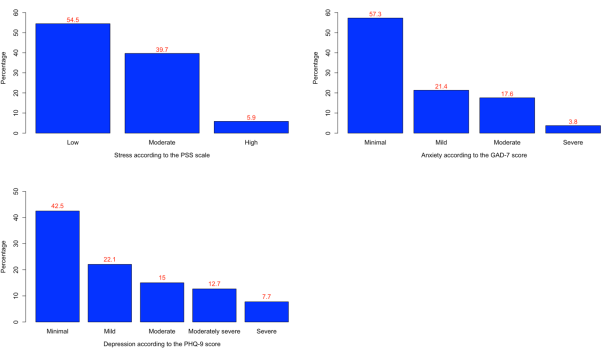
The mean score on the PSS was 13.8 (SD = 7.74), with a median score of 12 (range = 0-32). Moderate and high stress levels were observed in 39.7% and 5.9% of students, respectively. The mean GAD-7 score was 4.93 (SD = 4.82), with a median score of 3 (range = 0-17). Moderate and severe anxiety were reported by 17.6% and 3.8% of students, respectively. The mean PHQ-9 score was 7.72 (SD = 6.75), with a median score of 6 (range = 0-23). Moderate depression, moderately severe depression, and severe depression were in 15.0%, 12.7%, and 7.7% of students, respectively. Figure 2 illustrates the distribution of students based on the PSS, GAD-7, and PHQ-9 scales.
Figure 2. Distribution of students according to the PSS, GAD-7 score, and PHQ-9 score.
3.2. Analytical Results
3.2.1. Bivariate Analysis
Stress was significantly associated with male gender (OR = 2.02, 95%CI [1.37-2.99]), a history of chronic illness (OR = 2.39, 95%CI [1.22-4.87]), tobacco use (OR = 3.13, 95%CI [1.44-7.39]), and the use of sleeping pills (OR = 8.81, 95%CI [1.56-223]). Poor sleep quality (OR = 36.8, 95%CI [20.1-73.0]), low financial resources (OR = 25.7, 95%CI [15.5-44.0]), living alone OR = 11.4, 95%CI [6.27-22.4]), and poor diet (OR = 63.2, 95%CI [30.0-157]) were also significantly associated with stress. Additionally, low self-esteem (OR = 228, 95%CI [88.9-674]), and moderate self-esteem (OR = 17.8, 95%CI [8.61-42.0]), a negative emotional state (OR = 52.4, 95%CI [29.0-101]), absence of physical activity (OR = 19.4, 95%CI [12.0-32.2]), and a passive coping style (OR = 4.32, 95%CI [2.87-6.59]) were significantly associated with stress.
Anxiety was significantly associated with a history of chronic illness (OR = 2.45, 95%CI [1.20-4.85]), the use of sleeping pills (OR = 7.57, 95%CI [1.89-38.7]), poor sleep quality (OR = 36.9, 95%CI [18.4-83.1]), and low financial income (OR = 28.6, 95%CI [12.4-84.2]). Living alone (OR = 6.38, 95%CI [3.82-10.8]), poor diet (OR = 243, 95%CI [73.6-1706]), low self-esteem (OR = 303, 95%CI [64.5-7149]) or moderate self-esteem (OR = 8.29, 95%CI [1.50-208]), a negative emotional state (OR = 244, 95%CI [53.8-5700]), absence of physical activity (OR = 59.9, 95%CI [21.8-257]), and a passive coping style (OR = 21.0, 95%CI [9.14-61.7]) were also significantly associated with anxiety.
Depression was significantly associated with male gender (OR = 1.83, 95%CI [1.22-2.74]), a history of chronic illness (OR = 2.43, 95%CI [1.25-4.75]), tobacco use (OR = 3.13, 95%CI [1.48-6.87]), the use of sleeping pills (OR = 6.28, 95%CI [1.45-46.9]), poor sleep quality (OR = 41.2, 95%CI [23.6-75.1]), foreign nationality (OR = 1.76, 95%CI [1.13-2.76]), lack of family support (OR = 10.1, 95%CI [1.65-263]), low financial income (OR = 27.1, 95%CI [15.1-52.1]), living alone (OR = 9.83, 95%CI [5.80-17.2]), poor diet (OR = 79.5, 95%CI [41.7-163]), low self-esteem (OR = 308, 95%CI [101-1473]) or moderate self-esteem (OR = 20.6, 95%CI [7.26-89.5]), negative emotional state (OR = 49.6, 95%CI [27.5-94.4]), absence of physical activity (OR = 20.1, 95%CI [11.9-35.3]), and a passive coping style (OR = 4.62, 95%CI [2.97-7.33]). Table 2 presents the results of the bivariate analysis of stress, anxiety, and depression.
Table 2. Results of the bivariate analysis of stress, anxiety, and depression among CESAG students.

Stress

Variables

No N=232 n (%)

Yes N=194 n (%)

OR [95%CI]

p-value

Age group

0.053

<20 years

69 (63.3)

40 (36.7)

Ref.

[20-25 years [

81 (51.6)

76 (48.4)

1.61 [0.98-2.68]

[25-30 years [

61 (56.0)

48 (44.0)

1.35 [0.79-2.34]

≥30 years

21 (41.2)

30 (58.8)

2.44 [1.24-4.90]

Sex

0.001

Female

151 (61.9)

93 (38.1)

Ref.

Male

81 (44.5)

101 (55.5)

2.02 [1.37-2.99]

Chronic illness

0.015

No

218 (56.5)

168 (43.5)

Ref.

Yes

14 (35.0)

26 (65.0)

2.39 [1.22-4.87]

Tobacco

0.006

No

223 (56.5)

172 (43.5)

Ref.

Yes

9 (29.0)

22 (71.0)

3.13 [1.44-7.39]

Alcohol

0.205

No

180 (52.8)

161 (47.2)

Ref.

Yes

52 (61.2)

33 (38.8)

0.71 [0.43-1.15]

Sleeping pills

0.013

No

231 (55.4)

186 (44.6)

Ref.

Yes

1 (11.1)

8 (88.9)

8.81 [1.56-223]

Sleep quality

<0.001

Good

219 (78.5)

60 (21.5)

Ref.

Poor

13 (8.84)

134 (91.2)

36.8 [20.1-73.0]

Nationality

0.064

Senegalese

84 (61.3)

53 (38.7)

Ref.

Others

148 (51.2)

141 (48.8)

1.51 [1.00-2.29]

Financial income

<0.001

Good

189 (87.1)

28 (12.9)

Ref.

Low

43 (20.6)

166 (79.4)

25.7 [15.5-44.0]

Housing

<0.001

Shared accommodation or living with family

219 (65.6)

115 (34.4)

Ref.

Living alone

13 (14.1)

79 (85.9)

11.4 [6.27-22.4]

Diet

<0.001

Good

225 (77.9)

64 (22.1)

Ref.

Poor

7 (5.11)

130 (94.9)

63.2 [30.0-157]

Self-esteem

<0.001

High

146 (94.8)

8 (5.19)

Ref.

Low

8 (6.90)

108 (93.1)

228 [88.9-674]

Moderate

78 (50.0)

78 (50.0)

17.8 [8.61-42.0]

Emotional state

<0.001

Positive

216 (84.7)

39 (15.3)

Ref.

Negative

16 (9.36)

155 (90.6)

52.4 [29.0-101]

Physical activity

<0.001

Yes

193 (83.2)

39 (16.8)

Ref.

No

39 (20.1)

155 (79.9)

19.4 [12.0-32.2]

Coping style

<0.001

Active

141 (73.4)

51 (26.6)

Ref.

Passive

91 (38.9)

143 (61.1)

4.32 [2.87-6.59]

Anxiety

Variables

No N=335 n (%)

Yes N=91 n (%)

OR [95%IC]

p-value

Age group

0.180

<20 years

88 (80.7)

21 (19.3)

Ref.

[20-25 years [

129 (82.2)

28 (17.8)

0.91 [0.49-1.72]

[25-30 years [

83 (76.1)

26 (23.9)

1.31 [0.68-2.53]

≥30 years

35 (68.6)

16 (31.4)

1.91 [0.88-4.10]

Sex

0.114

Female

199 (81.6)

45 (18.4)

Ref.

Male

136 (74.7)

46 (25.3)

1.49 [0.94-2.39]

Chronic illness

0.016

No

310 (80.3)

76 (19.7)

Ref.

Yes

25 (62.5)

15 (37.5)

2.45 [1.20-4.85]

Tobacco

0.393

No

313 (79.2)

82 (20.8)

Ref.

Yes

22 (71.0)

9 (29.0)

1.57 [0.66-3.47]

Alcohol

0.094

No

262 (76.8)

79 (23.2)

Ref.

Yes

73 (85.9)

12 (14.1)

0.55 [0.27-1.04]

Sleeping pills

0.004

No

332 (79.6)

85 (20.4)

Ref.

Yes

3 (33.3)

6 (66.7)

7.57 [1.89-38.7]

Sleep quality

<0.001

Good

270 (96.8)

9 (3.23%)

Ref.

Poor

65 (44.2)

82 (55.8)

36.9 [18.4-83.1]

Nationality

0.341

Senegalese

112 (81.8)

25 (18.2)

Ref.

Others

223 (77.2)

66 (22.8)

1.32 [0.80-2.24]

Religion

0.026

Islam

200 (81.6)

45 (18.4)

Ref.

Christianity

132 (75.9)

42 (24.1)

1.41 [0.88-2.28]

Others

3 (42.9)

4 (57.1)

5.80 [1.17-32.4]

Marital status

0.278

Married

23 (69.7)

10 (30.3)

Ref.

Unmarried

312 (79.4)

81 (20.6)

0.59 [0.28-1.36]

Financial income

<0.001

Good

212 (97.7)

5 (2.30)

Ref.

Low

123 (58.9)

86 (41.1)

28.6 [12.4-84.2]

Housing

<0.001

Shared accommodation or living with family

289 (86.5)

45 (13.5)

Ref.

Living alone

46 (50.0)

46 (50.0)

6.38 [3.82-10.8]

Diet

<0.001

Good

287 (99.3)

2 (0.69)

Ref.

Poor

48 (35.0)

89 (65.0)

243 [73.6-1706]

Self-esteem

<0.001

High

153 (99.4)

1 (0.65)

Ref.

Low

35 (30.2)

81 (69.8)

303 [64.5-7149]

Moderate

147 (94.2)

9 (5.77)

8.29 [1.50-208]

Emotional state

<0.001

Positive

254 (99.6)

1 (0.39)

Ref.

Negative

81 (47.4)

90 (52.6)

244 [53.8-5700]

Physical activity

<0.001

Yes

229 (98.7)

3 (1.29)

Ref.

No

106 (54.6)

88 (45.4)

59.9 [21.8-257]

Coping style

<0.001

Active

187 (97.4)

5 (2.60)

Ref.

Passive

148 (63.2)

86 (36.8)

21.0 [9.14-61.7]

Depression

Variables

No N=275 n (%)

Yes N=151 n (%)

OR [95%IC]

p-value

Age group

0.052

<20 years

77 (70.6)

32 (29.4)

Ref.

[20-25 years [

105 (66.9)

52 (33.1)

1.19 [0.70-2.04]

[25-30 years [

68 (62.4)

41 (37.6)

1.45 [0.82-2.57]

≥30 years

25 (49.0)

26 (51.0)

2.48 [1.25-4.99]

Sex

0.004

Female

172 (70.5)

72 (29.5)

Ref.

Male

103 (56.6)

79 (43.4)

1.83 [1.22-2.74]

Chronic illness

0.011

No

257 (66.6)

129 (33.4)

Ref.

Yes

18 (45.0)

22 (55.0)

2.43 [1.25-4.75]

Tobacco

0.003

No

263 (66.6)

132 (33.4)

Ref.

Yes

12 (38.7)

19 (61.3)

3.13 [1.48-6.87]

Alcohol

0.154

No

214 (62.8)

127 (37.2)

Ref.

Yes

61 (71.8)

24 (28.2)

0.67 [0.39-1.11]

Sleeping pills

0.011

No

273 (65.5)

144 (34.5)

Ref.

Yes

2 (22.2)

7 (77.8)

6.28 [1.45-46.9]

Sleep quality

<0.001

Good

250 (89.6)

29 (10.4)

Ref.

Poor

25 (17.0)

122 (83.0)

41.2 [23.6-75.1]

Nationality

0.016

Senegalese

100 (73.0)

37 (27.0)

Ref.

Others

175 (60.6)

114 (39.4)

1.76 [1.13-2.76]

Religion

0.410

Islam

157 (64.1)

88 (35.9)

Ref.

Christianity

115 (66.1)

59 (33.9)

0.92 [0.61-1.38]

Others

3 (42.9)

4 (57.1)

2.34 [0.48-13.0]

Marital status

0.150

Married

17 (51.5)

16 (48.5)

Ref.

Unmarried

258 (65.6)

135 (34.4)

0.56 [0.27-1.15]

Family support

0.009

Yes

274 (65.4)

145 (34.6)

Ref.

No

1 (14.3)

6 (85.7)

10.1 [1.65-263]

Financial income

<0.001

Good

203 (93.5)

14 (6.45)

Ref.

Low

72 (34.4)

137 (65.6)

27.1 [15.1-52.1]

Housing

<0.001

Shared accommodation or living with family

253 (75.7)

81 (24.3)

Ref.

Living alone

22 (23.9)

70 (76.1)

9.83 [5.80-17.2]

Diet

<0.001

Good

261 (90.3)

28 (9.69)

Ref.

Poor

14 (10.2)

123 (89.8)

79.5 [41.7-163]

Self-esteem

<0.001

High

151 (98.1)

3 (1.95)

Ref.

Low

15 (12.9)

101 (87.1)

308 [101-1473]

Moderate

109 (69.9)

47 (30.1)

20.6 [7.26-89.5]

Emotional state

<0.001

Positive

238 (93.3)

17 (6.67)

Ref.

Negative

37 (21.6)

134 (78.4)

49.6 [27.5-94.4]

Physical activity

<0.001

Yes

211 (90.9)

21 (9.05)

Ref.

No

64 (33.0)

130 (67.0)

20.1 [11.9-35.3]

Coping style

<0.001

Active

158 (82.3)

34 (17.7)

Ref.

Passive

117 (50.0)

117 (50.0)

4.62 [2.97-7.33]

3.2.2. Multivariate Analysis
The predictive model for stress had a sensitivity of 91.1% (95%CI [87.1-95.2]) and a specificity of 94.3% (95%CI [91.3-97.3]). Stress was associated with age group: students aged [20-25 years[ (ORa = 5.68, 95%CI [1.67-19.31]) and those ≥ 30 years (ORa = 8.8, 95%CI [1.5-51.64]) were more likely to experience stress compared to those under 20 years. Other risk factors for stress included poor sleep quality (ORa = 7.05, 95%CI [2.32-21.44]), low financial income (ORa = 11.23, 95%CI [4.34-29.06]), low self-esteem (ORa = 15.13, 95%CI [3.18-72.13]) or moderate self-esteem (ORa = 7.96, 95%CI [2.83-22.4]), negative emotional state (ORa = 4.7, 95%CI [1.64-13.46]), and absence of physical activity (ORa = 5.03, 95%CI [1.88-13.49]).
The predictive model for anxiety had a sensitivity of 73.0% (95%CI [63.8-82.3]) and a specificity of 4.2% (95%CI [2.1-6.4]). Living alone was identified as a protective factor against anxiety (ORa = 0.16, 95%CI [0.09-0.29]).
The predictive model for depression had a sensitivity of 91.2% (95%CI [86.7-95.8]) and a specificity of 94.5% (95%CI [91.8-97.2]). Risk factors for depression included poor sleep quality (ORa = 8.07, 95%CI [2.72-23.88]), low financial income (ORa = 4.38, 95%CI [1.42-13.48]), living alone (ORa = 3.53, 95%CI [1.1-11.34]), poor diet (ORa = 13.03, 95%CI [3.84-44.18]), low self-esteem (ORa = 18.21, 95%CI [2.62-126.41]) or moderate self-esteem (ORa = 9.19, 95%CI [1.66-51.01]), and negative emotional state (ORa = 5.54, 95%CI [1.64-18.71]). A passive coping style was found to be a protective factor against depression (ORa = 0.25, 95%CI [0.08-0.8]). Table 3 presents the results of the multivariate analysis of predictive factors for stress, anxiety, and depression.
Table 3. Results of the multivariate analysis of predictive factors for stress, anxiety, and depression among CESAG students.

Variables

Adjusted OR

95%CI

p-value

Stress: Yes vs No (Ref.)

Age group: Ref.= <20 years

0.006

[20-25 years [

5.68

[1.67-19.31]

[25-30 years [

1.66

[0.47-5.8]

≥30 years

8.8

[1.5-51.64]

Sex: Male vs Female (Ref.)

1.95

[0.83-4.56]

0.122

Sleep quality: Poor vs Good (Ref.)

7.05

[2.32-21.44]

< 0.001

Nationality: Others vs Senegalese (Ref.)

0.44

[0.16-1.17]

0.096

Religion: Ref. = Islam

0.002

Christianity

0.25

[0.09-0.71]

Others

39.55

[1.29-1210.19]

Financial income: Low vs Good (Ref.)

11.23

[4.34-29.06]

< 0.001

Housing: Living alone vs Shared accommodation or living with family (Ref.)

3.09

[0.91-10.41]

0.067

Self-esteem: Ref. = High

< 0.001

Moderate

7.96

[2.83-22.4]

Low

15.13

[3.18-72.13]

Emotional state: Negative vs Positive (Ref.)

4.7

[1.64-13.46]

0.004

Physical activity: No vs Yes (Ref.)

5.03

[1.88-13.49]

0.001

Anxiety: Yes vs No (Ref.)

Age group: Ref.= <20 years

0.541

[20-25 years [

1.38

[0.67-2.82]

[25-30 years [

1.07

[0.5-2.31]

≥30 years

0.76

[0.31-1.83]

Sex: Male vs Female (Ref.)

0.7

[0.41-1.2]

0.194

Chronic illness: Yes vs No (Ref.)

0.67

[0.29-1.56]

0.358

Alcohol: Yes vs Non (Ref.)

1.95

[0.9-4.24]

0.078

Sleeping pills: Yes vs No (Ref.)

0.25

[0.05-1.27]

0.085

Nationality: Others vs Senegalese (Ref.)

1.6

[0.83-3.06]

0.158

Religion: Ref. = Islam

0.158

Christianity

0.79

[0.45-1.39]

Others

0.19

[0.03-1.09

Marital status: Unmarried vs Married (Ref.)

1.41

[0.54-3.63]

0.487

Housing: Living alone vs Shared accommodation or living with family (Ref.)

0.16

[0.09-0.29]

< 0.001

Depression: Yes vs No (Ref.)

Age group: Ref. = <20 years

0.067

[20-25 years [

1.64

[0.44-6.13]

[25-30 years [

2.39

[0.58-9.82]

≥30 years

8.85

[1.54-50.98]

Sleep quality: Poor vs Good (Ref.)

8.07

[2.72-23.88]

< 0.001

Religion: Ref. = Islam

< 0.001

Christianity

0.13

[0.04-0.4]

Others

1.35

[0-402.11]

Family support: Yes vs No (Ref.)

0.1

[0.01-1.36]

0.135

Financial income: Low vs Good (Ref.)

4.38

[1.42-13.48]

0.009

Housing: Living alone vs Shared accommodation or living with family (Ref.)

3.53

[1.1-11.34]

0.031

Diet: Poor vs Good (Ref.)

13.03

[3.84-44.18]

< 0.001

Self-esteem: Ref. = High

0.003

Moderate

9.19

[1.66-51.01]

Low

18.21

[2.62-126.41]

Emotional state: Negative vs Positive (Ref.)

5.54

[1.64-18.71]

0.005

Coping style: Passive vs Active (Ref.)

0.25

[0.08-0.8]

0.012

4. Discussion
On stress and its associated factors
In our study, 45.6% of students reported experiencing stress, with 5.9% presenting high stress levels. These findings align with previous research. Melaku et al. identified stress symptoms in 40.4% of respondents at Arsi University, Ethiopia, in 2021, including 2.3% with extremely severe symptoms. Similarly, Amamou et al. found that 63.9% of medical students at the University of Sousse, Tunisia, reported high perceived stress in 2022. In Senegal, Mansouri et al. estimated the stress prevalence at 15.2% in the general population during the COVID-19 pandemic.
Key risk factors of stress identified in our study included being in the [20-25 years[ age group or aged over 30 and above, poor sleep quality, low financial income, low or moderate self-esteem, negative emotional state, and absence of physical activity.
Several studies have explored the relationship between age and stress in students. Research generally indicates that younger students experience higher stress levels than their older peers, possibly due to a lack of experience, adaptation difficulties, time management challenges, and academic pressure . However, older or more advanced students may also face significant stress due to increased academic workload, higher performance expectations, uncertainty about future employment, and financial constraints. Variations in findings may be attributed to differences in participant inclusion criteria and educational contexts.
Sleep deprivation and poor sleep quality are well-established contributors to stress, as they disrupt emotional regulation processes . In 2010, Lund et al. found that university students with poor sleep quality reported significantly higher stress levels than their well-rested peers in a Midwest urban setting. A 2024 meta-analysis by Nakie et al. confirmed a strong association between poor sleep quality and stress among African university students. Using the Pittsburgh Sleep Quality Index (PSQI), Amamou et al. reported that poor sleep quality is independently associated with high levels of perceived stress (OR = 9.062). Sleep deprivation or sleep disorders such as insomnia may amplify stress perception and reduce resilience in the face of daily challenges.
Financial difficulties are another well-documented stressor among students. Melaku et al. found that students with a monthly income ≤ 700 ETB (Ethiopian Birr) were more likely to experience stress compared to those with a monthly income > 700 ETB (OR = 1.87). Similarly, Pretorius and Blaauw reported that financial difficulties negatively affect students’ subjective well-being at a comprehensive South African university. These findings suggest that financial constraints contribute to student stress beyond academic pressures.
Stress has also been linked to self-esteem and emotional state . Mann et al. reported that individuals with low self-esteem are less able to manage stress effectively, as they are more likely to interpret events as threatening and have a pessimistic view of their ability to cope. Gross et al. observed that individuals who frequently experience negative emotions, such as anger, sadness, or worry, are more prone to stress. These emotions can limit their ability to employ effective coping strategies and exacerbate their stress response.
Finally, physical activity has been associated with lower stress levels. Gerber et al. reported that students who engaged in regular physical activity exhibited lower stress levels. Similarly, Johannes et al. found significant correlations between mental health subscales and total physical activity volume, specifically anxiety (r = 0.10) and stress (r = 0.11), among South African undergraduate students. These findings suggest that physical activity enhances mood, reduces mental fatigue, and improves sleep quality, thereby supporting better stress management .
On anxiety and its associated factors
In our study, 21.4% of students experienced anxiety, with 3.8% showing severe symptoms. Melaku et al. reported anxiety in 60.8% of respondents, with 16.2% with severe symptoms, while Amamou et al. observed anxiety symptoms in 36.1% of respondents. In Senegal, Mansouri et al. found a 5.1% prevalence of anxiety in the general population during the COVID-19 pandemic.
The lower proportion of anxious students in our study may be related to the online data collection method, which could have discouraged anxious individuals from participating. Additionally, the higher prevalence reported by Melaku et al. may be due to differences in the self-assessment tools. Melaku et al. used the DASS-21 (Depression Anxiety Stress Scale-21), which evaluates emotional states of depression, anxiety, and stress over the past week, whereas Amamou et al. used the HADS-10 (Hospital Anxiety and Depression Scale-10), that includes separate subscales for anxiety (HAD-A) and depression (HAD-D). Consequently, the GAD-7 (used in our study) and the HAD-A may have been more specific in detecting anxiety, potentially reducing false positives compared to the DASS-21.
Furthermore, our study found that living alone was a protective factor against anxiety. Students living alone reported significantly lower anxiety levels compared to those living with roommates or family. This finding contrasts with existing literature, which generally links living alone to a higher risk of anxiety due to social isolation . This discrepancy may result from the underrepresentation of anxious individuals in our sample, as the online data collection method could have acted as a barrier, discouraging more anxious students from participating. Consequently, this may have led to an underestimation of the association between living alone and anxiety. Alternatively, it may reflect a unique academic context, where students frequently engage in social interactions outside the home, mitigating the potential negative effects of living alone.
On depression and its associated factors
In our study, 35.4% of students exhibited depressive symptoms, with 7.7% experiencing severe symptoms. In comparison, Melaku et al. reported a prevalence of 52.3%, including 6.2% with severe symptoms, while Amamou et al. found depressive symptoms in 22.3% of students. In Senegal, Mansouri et al. reported a 13.4% prevalence of depression in the general population during the COVID-19 pandemic. Differences in prevalence rates across studies may be partly explained by variations in the self-assessment tools used. The PHQ-9 (used in our study) and HAD-D may have been more specific in screening for depression than the DASS-21, potentially reducing false positives.
Several risk factors for depression were identified in our study, including poor sleep quality, low financial income, living alone, poor diet, low or moderate self-esteem, and a negative emotional state. A passive coping style was found to be a protective factor.
Sleep disturbances, particularly poor sleep quality and insomnia, are well-documented contributors to depression in students . Coelho et al. , in a two-year cohort study, demonstrated this link by highlighting two aspects: first, insomnia as a risk factor for the onset of depressive symptoms in initially asymptomatic students, and second, daytime sleepiness in already symptomatic students, which contributes to the persistence of depressive symptoms. Similarly, a meta-analysis by Bi et al. confirmed that sleep disturbances, including both insomnia and excessive sleepiness, are significantly associated with depressive symptoms.
The role of socio-economic status in mental health is widely recognized. Melaku et al. identified low monthly income as a risk factor for depression, a finding supported by a meta-analysis by Richardson et al. , which reported that students facing financial difficulties are more likely to exhibit depressive symptoms. Eisenberg et al. found that American students facing financial constraints were more prone to developing depressive symptoms. Similarly, Hunt et al. demonstrated that financial pressures increase vulnerability to mental health disorders due to daily worries and limitations they impose on social interactions and overall quality of life.
Loneliness is another key determinant of depression among students, as social and family networks play a crucial protective role . Melaku et al. found that students living outside dormitories were more likely to experience depression than those residing in dormitories. A meta-analysis by Santini et al. confirmed that social isolation and loneliness significantly increase depression risk, a finding reinforced by Wu et al. , who reported that individuals living alone had a higher likelihood of depression compared to those in shared accommodations. These results highlight the importance of social interactions in mitigating psychological distress, particularly in the university setting, where students navigate major life transitions and academic demands. Students living alone lack the daily social support that shared housing or family environments provide, making them more vulnerable to stress and depressive symptoms.
Diet quality has also been associated with depression. A systematic review by Lassale et al. found that adherence to a healthy diet, particularly the traditional Mediterranean diet, and avoiding pro-inflammatory foods are linked to a lower risk of depressive symptoms or clinical depression. Jacka et al. similarly reported that young adults with a low-quality diet characterized by high consumption of sugars, saturated fats, and processed foods had higher rates of depression. These findings suggest an association between diet quality and adolescent depression that exists over and above the influence of socioeconomic, family, and other potential confounding factors.
Self-esteem is another well-established factor in depression . Sowislo et al. identified low self-esteem as a significant predictor of depression, rather than merely a consequence of it. This relationship is particularly strong among young adults, including students, for whom self-esteem plays a crucial role in managing academic and social challenges. Sargent et al. examined self–worth contingencies and vulnerability to depressive symptoms in 629 college freshmen over their first semester. They found that higher reliance on external self–worth (based on approval from others, appearance, competition, and academics) predicted increased depressive symptoms, even after controlling for initial level of depressive symptoms, social desirability, gender, and race.
Negative emotional states are closely linked to depression . Kupferberg et al. found that negative emotional states, such as sadness, irritability, and anxiety, are strongly associated with depressive symptoms. Similarly, Eisenberg et al. reported that students experiencing high levels of stress, anger, or other negative emotions had higher levels of depressive symptoms. These findings suggest that academic and social stressors in student life contribute to emotional distress, increasing the risk of depression in this population.
The literature provides diverse perspectives on the effectiveness of coping styles. Most research suggests that active coping strategies (such as problem-solving) are generally more effective in reducing psychological distress, whereas passive coping styles (such as avoidance or submission) are often associated with higher levels of depression and anxiety . Compas et al. found that the maladaptive coping, disengagement coping, and strategies such as emotional suppression, avoidance, and denial are associated with increased psychopathology symptoms, indicating that they act more as risk factors than protective mechanisms. However, there may be circumstances in which passive coping is perceived as protective, particularly in situations where individuals have little or no control over events, and avoidance temporarily alleviates emotional distress. This was highlighted in the study by Holahan et al. , which found that in certain contexts, passive coping could reduce short-term stress. However, this should not be mistaken for a long-term protective effect against depression .
Strengths and limitations
This study investigates key factors associated with stress, anxiety, and depression in students. The use of validated screening tools (PSS, GAD-7, and PHQ-9) enhances the reliability of the findings.
The main limitations include not reaching the target sample size (426 respondents instead of the expected of 605) and relying exclusively on online data collection. The smaller-than-expected sample size may have increased the risk of type 1 errors. Moreover, online data collection could have discouraged participation among anxious individuals, potentially leading to their underrepresentation and influencing associations between anxiety and related factors.
Future research could build on these findings through a cohort study to better explore causal relationships between stress, anxiety, depression and their determinants among students at the institution.
5. Conclusion
Stress, anxiety, and depression are major concerns that can significantly impact students’ mental health, affecting both their well-being and academic performance. This research aimed to identify factors associated with these anxiety-depressive states among CESAG students, who are trained in a demanding academic environment.
This cross-sectional, observational, descriptive and analytical study was conducted from July 22 to August 23, 2024. The sample consisted of 426 students of both genders, regularly enrolled at the institution during the 2023-2024 academic year. Stress, anxiety, and depression were assessed using self-reported questionnaires: the Perceived Stress Scale (PSS) for stress, the Generalized Anxiety Disorder-7 (GAD-7) for anxiety, and the Patient Health Questionnaire-9 (PHQ-9) for depression.
The methodological limitations of the study included the failure to reach the calculated sample size, which increased the risk of type 1 errors, and the exclusive use of online data collection, which may have deterred participation, particularly among anxious individuals.
Our findings highlight the need for preventive strategies to enhance students’ mental health and well-being, particularly through awareness campaigns and initiatives designed to strengthen psychological support and prevention.
Abbreviations

AIC

Akaike Information Criterion

AUC

Area Under Curve

BCEAO

Central Bank of West African States

CESAG

African Center for Higher Studies in Management

DASS-21

Depression Anxiety Stress Scale-21

DSM

Department of Mental Health

DSP

Public Health Department

ETB

Ethiopian Birr

ESEA

Higher School of Applied Economics

FMPO

Faculty of Medicine, Pharmacy, and Dentistry

GAD-7

Generalized Anxiety Disorder-7

HADS-10

Hospital Anxiety and Depression Scale-10

CI

Confidence Interval

ISED

Institute of Health and Development

MSAS

Ministry of Health and Social Action

OR

Odds-ratio

ORa

Adjusted Odds-ratio

PHQ-9

Patient Health Questionnaire-9

PSQI

Pittsburgh Sleep Quality Index

PSS

Perceived Stress Scale

ROC

Receiver Operating Characteristic

SD

Standard Deviation

UCAD

Cheikh Anta DIOP University

VIF

Variance Inflation Factor (VIF)

Acknowledgments
We, authors of this manuscript, extend our sincere gratitude to the leadership of the African Center for Higher Studies in Management (CESAG) for its invaluable support in facilitating this research. We also express our deep appreciation to the students who graciously agreed to participate in the study. Our gratitude further extends to the ten students who actively contributed to the dissemination of information, thereby enhancing engagement in the selected classrooms. Moreover, we acknowledge the academic staff of the Institute of Health and Development (ISED) for their guidance and invaluable support throughout this work. Finally, we convey our profound thanks to the Public Health Department (DSP) of the Pasteur Institute of Dakar (IPD) for their keen interest in this research and the assistance they provide in its completion.
Author Contributions
Gad Papin Oholiab Namndiro: Conceptualization, design, Methodology, Investigation, Data management, Formal analysis, interpretation, Writing – original draft, Validation
Jean Augustin Diégane Tine: Conceptualization, design, methodology, Data management, Formal analysis, interpretation, writing – review & editing, and validation
Abdourahmane Sow: Funding acquisition, Project administration, Writing – review & editing, and validation
Ibrahima Seck: Project administration, Supervision, Writing – review & editing, Validation
Disclaimer
The views and opinions expressed in this article are those of the authors and do not necessarily reflect the official policy or position of any affiliated agency of the authors.
Funding
This research was entirely self-funded by the authors, with no financial contributions from any individual, organization, or institution at any stage of the study. All expenses were covered exclusively by the authors, ensuring the integrity and independence of the research process. No external funding or sponsorship was received for the completion of this work.
Data Availability Statement
Datasets presented in this article are available from the corresponding author upon reasonable request.
Conflicts of Interest
We, authors of this manuscript, solemnly declare that there are no conflicts of interest among us regarding this publication.
Appendix
Annex: Questionnaire overview
Chapter 1: information on the biological dimension
1. What is your age? _____________________
2. What is your sex?
o Male
o Female
3. Do you have any significant medical history? (Check all that apply)
o None
o Psychiatric disorders
o Chronic illness (e.g., diabetes, high blood pressure, etc.)
o Other (please specify): _____________________
4. Do you smoke tobacco?
o Yes, regularly (several times per week)
o Yes, occasionally (once in a while)
o No (never)
5. Do you drink alcohol?
o Yes, regularly (several times per week)
o Yes, occasionally (once in a while)
o No (never)
6. Do you use sleeping pills to help to sleep?
o Yes, regularly (several times per week)
o Yes, occasionally (once in a while)
o No (never)
7. How would you rate your overall sleep quality over the past month, considering factors such as total sleep duration, sleep depth, and frequency of nighttime awakenings?)
o Very poor
o Poor
o Average
o Good
o Very good
Chapter 2: information on the social context
8. What is your current marital status?
o Single
o Married
o Divorced
o Widowed
9. What is your nationality?
o Senegalese
o Ivorian
o Burkinabe
o Bissau-Guinean
o Beninese
o Nigerien
o Other (please specify): _____________________
10. What is your religion?
o Islam
o Christianity
o None
o Other (please specify): _____________________
11. Do you receive family support in your studies?
o Yes, regularly
o Yes, occasionally
o No
12. How would you rate your financial income level?
o Very low
o Low
o Average
o Good
o Very good
13. What is your current housing situation?
o Living alone
o Shared accommodation (living with roommates)
o Living with family
14. How would you rate the quality of your diet?
o Very poor
o Poor
o Average
o Good
o Very good
Chapter 3: information on the psychological dimension
15. On a scale from 1 to 10, how would you rate your self-esteem? (1 being very low and 10 being very high) _____________________
16. How would you describe your emotional state over the past two weeks?
o Very negative
o Somewhat negative
o Neutral
o Somewhat positive
o Very positive
17. Do you engage in physical activity?
o Yes, regularly (several times per week)
o Yes, occasionally (once in a while)
o No (never)
18. What is your usual approach to dealing with problems?
Distance yourself from the problem
o Ask for help from others
o Ignore or repress the problem
o Actively seek for a solution
o Use a psychoactive substance to forget the problem (alcohol, tobacco, sleeping pills, etc.)
o Practice sports or meditation
o Other (please specify): _____________________
Chapter 4: information on variables of interest
Perceived Stress Scale
Scoring: never = 0 point, almost never = 1point, sometimes = 2 points, often = 3 points, very often = 4 points *= reverse scoring (from never = 4 points to very often = 0 point)
19. Over the past month, how often have you been upset because of an unexpected event?
o Never
o Almost never
o Sometimes
o Often
o Very often
20. Over the past month, how often have you felt that you were unable to control the important things in your life?
o Never
o Almost never
o Sometimes
o Often
o Very often
21. Over the past month, how often have you felt nervous and stressed?
o Never
o Almost never
o Sometimes
o Often
o Very often
22. *Over the past month, how often have you felt confident in your ability to handle your personal problems?
o Never
o Almost never
o Sometimes
o Often
o Very often
23. *Over the past month, how often have you felt that things were going your way?
o Never
o Almost never
o Sometimes
o Often
o Very often
24. Over the past month, how often have you found that you could not cope with all the things you had to do?
o Never
o Almost never
o Sometimes
o Often
o Very often
25. *Over the past month, how often have you been able to control irritations in your life?
o Never
o Almost never
o Sometimes
o Often
o Very often
26. *Over the past month, how often have you felt that you were in control of things?
o Never
o Almost never
o Sometimes
o Often
o Very often
27. Over the past month, how often have you been upset because of things that happened that were outside your control?
o Never
o Almost never
o Sometimes
o Often
o Very often
28. Over the past month, how often have you felt that difficulties were piling up so high that you could not overcome them?
o Never
o Almost never
o Sometimes
o Often
o Very often
Generalized Anxiety Disorder-7
Scoring: not at all = 0 point, several days = 1point, more than half of the days = 2 points, nearly every day = 3 points
29. Over the last two weeks, how often have you been bothered by the following problems?
Feeling nervous, anxious, or on edge:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Being unable to stop worrying or control your worries:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Worrying too much about different things:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Having difficulty relaxing:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Being so restless that it is hard to sit still:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Becoming easily annoyed or irritable:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Feeling afraid, as if something awful might happen:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Patient Health Questionnaire-9
Scoring: not at all = 0 point, several days = 1 point, more than half of the days = 2 points, nearly every day = 3 points
30. Over the past two weeks, how often have you been bothered by any of the following problems?
Little interest or pleasure in doing things:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Feeling down, depressed, or hopeless:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Trouble falling or staying asleep, or sleeping too much:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Feeling tired or having little energy:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Poor appetite or overeating:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Feeling bad about yourself, or that you are a failure or have let yourself or your family down:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Trouble concentrating on things, such as reading a document or watching television:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Moving or speaking so slowly that other people could have noticed. Or the opposite -being so figety or restless that you have been moving around more than usual:
o Not at all
o Several days
o More than half of the days
o Nearly every day
Thoughts that you would be better off dead, or of hurting yourself:
o Not at all
o Several days
o More than half of the days
o Nearly every day
References
[1] Melaku L, Bulcha G, Worku D. Stress, Anxiety, and Depression among Medical Undergraduate Students and Their Coping Strategies. Educ Res Int. 2021; 2021(1): 9880309.
[2] Radeef AS, Faisal GG, Ali SM, Ismail MKHM. Source of stressors and emotional disturbances among undergraduate science students in Malaysia. Int J Med Res Health Sci. 2014; 3(2): 401.
[3] Strenna L, Chahraoui K, Vinay A. Santé psychique chez les étudiants de première année d’école supérieure de commerce: liens avec le stress de l’orientation professionnelle, l’estime de soi et le coping. Orientat Sc Prof. 2009 Jun 15; (38/2): 183–204.
[4] Hm A, Aa A, Es M, Gg P, Ea A. Stress and its effects on medical students: a cross-sectional study at a college of medicine in Saudi Arabia. J Health Popul Nutr [Internet]. 2011 Oct [cited 2025 Mar 25]; 29(5). Available from:
[5] NECHITA F, STREBA CT, VERE CC, NECHITA D, ROGOVEANU I. Stress in Romanian First Year Nursing Students. Curr Health Sci J. 2014; 40(3): 210–3.
[6] Sarkar S, Gupta R, Menon V. A Systematic Review of Depression, Anxiety, and Stress among Medical Students in India. J Ment Health Hum Behav. 2017 Dec; 22(2): 88.
[7] Amamou B, Ben Saida I, Bejar M, Messaoudi D, Gaha L, Boussarsar M. Stress, anxiété et dépression chez les étudiants à la faculté de médecine de Sousse (Tunisie). Tunis Médicale. 2022 Apr; 100(4): 346–52.
[8] Stallman HM. Psychological distress in university students: A comparison with general population data. Aust Psychol. 2010; 45(4): 249–57.
[9] Eisenberg D, Hunt J, Speer N. Mental health in American colleges and universities: variation across student subgroups and across campuses. J Nerv Ment Dis. 2013 Jan; 201(1): 60–7.
[10] Quels sont les facteurs de stress des étudiant-es? Analyse quantitative et qualitative des sources de stress des étudiant-es. Observatoire de la Vie Etudiante 2023. Université de Génève.pdf [Internet]. [cited 2025 Mar 25]. Available from:
[11] Prince M, Patel V, Saxena S, Maj M, Maselko J, Phillips MR, et al. No health without mental health. The Lancet. 2007 Sep 8; 370(9590): 859–77.
[12] Petit V. Circulations et quêtes thérapeutiques en santé mentale au Sénégal. Rev Francoph Sur Santé Territ [Internet]. 2019 Dec 16 [cited 2025 Mar 25]; Available from: h
[13] Sy A, Tine JAD, Diallo A, Diagne N, Toure K, Seck I, et al. Study of Factor Associated with Post Stroke Depression in the Teaching Hospital of Fann (Dakar-Senegal). Health (N Y). 2019 Jan 1; 11: 1518–28.
[14] Tine JAD, Youssouf T, Makhtar BEH, Cheikh SM, Babacar S, Cambel DA, et al. Study of risk factors for posttraumatic stress disorder (PTSD) among Senegalese peacekeepers on a mission of peacekeeping in Darfur. Int J Innov Appl Stud. 2019 May 2; 26(2): 486–97.
[15] Ba EHM, Ba F, Tine JAD, Thiam MH. Burn out des troupes sénégalaises engagées dans les opérations extérieures: cas de la mission de maintien de la paix au Darfour. [Internet]. [cited 2025 Mar 25]; Available from:
[16] Sy A, Kokou EK, Tine JAD, Sy NAM, Diallo A, Seck I, et al. Study of Descriptive Determinants of Moral Harassment at Work in a Factory in Senegal. Health (N Y). 2020 Jan 21; 12(2): 106–17.
[17] Sy A, Tine JAD, Benmansour S, Mamadou SO, Binta B, Aissatou D, et al. Sickle Cell Patient and Addiction to Tramadol: Case Management in Senegal. Health (N Y). 2020 Jan 21; 12(2): 99–105.
[18] Mansouri F, Lahlou L, Camara M, Seck S, Ba EHM, Thiam MH. Les niveaux d’impact psychologique, d’anxiété, de dépression et de stress de la population générale du Sénégal pendant la pandémie de COVID-19. Ann Med Psychol (Paris) [Internet]. 2022 Sep 6 [cited 2025 Apr 2]; Available from:
[19] Diagne I, Petit V, Ndiaye-Ndongo ND, Sylla A. Profile of young Senegalese aged 15 to 25 years with mental health problems: a study from the Dalal Xel mental health center of Thies. Health Sci Dis [Internet]. 2023 May 31 [cited 2025 Apr 2]; 24(6). Available from:
[20] Ndong A, Togtoga L, Bah MS, Ndoye PD, Tine JAD, Konaté I, et al. Burn-out among practitioners managing abdominal surgical emergencies in Senegal. J Med Surg Public Health. 2024 Apr 1; 2: 100087.
[21] Ministère de la Santé et de l’Action Sociale. Plan National de Développement Sanitaire et Social (PNDSS) 2019-2028. 2019.pdf [Internet]. [cited 2025 Mar 25]. Available from:
[22] Tine, JAD. (2019). Rapport d’activité 2018 de la Division de la Santé Mentale et perspectives 2019-2020, Sénégal.pdf [Internet]. [cited 2025 Mar 25]. Available from:
[23] Centre Africain d’Etudes Supérieures en Gestion - CESAG [Internet]. [cited 2025 Mar 25]. Available from:
[24] Cohen, S., & Williamson, G. (1988). Perceived stress in a probability sample of the United States. In S. Spacapan & S. Oskamp (Eds.), The social psychology of health: Claremont Symposium on Applied Social Psychology (pp. 31–67). Newbury Park, CA: Sage.pdf [Internet]. [cited 2025 Mar 25]. Available from:
[25] Spitzer RL, Kroenke K, Williams JBW, Löwe B. A Brief Measure for Assessing Generalized Anxiety Disorder: The GAD-7. Arch Intern Med. 2006 May 22; 166(10): 1092–7.
[26] Spitzer RL, Kroenke K, Williams JBW, and the Patient Health Questionnaire Primary Care Study Group. Validation and Utility of a Self-report Version of PRIME-MDThe PHQ Primary Care Study. JAMA. 1999 Nov 10; 282(18): 1737–44.
[27] RStudio Team. (2024). RStudio: Integrated Development Environment for R (Version 2024.12.1.563) [Logiciel]. RStudio, PBC.
[28] Mofatteh M. Risk factors associated with stress, anxiety, and depression among university undergraduate students. AIMS Public Health. 2020 Dec 25; 8(1): 36–65.
[29] Lund HG, Reider BD, Whiting AB, Prichard JR. Sleep patterns and predictors of disturbed sleep in a large population of college students. J Adolesc Health Off Publ Soc Adolesc Med. 2010 Feb; 46(2): 124–32.
[30] Nakie G, Takelle GM, Rtbey G, Andualem F, Tinsae T, Kassa MA, et al. Sleep quality and associated factors among university students in Africa: a systematic review and meta-analysis study. Front Psychiatry. 2024 Mar 11; 15: 1370757.
[31] Pretorius M, Blaauw D. Financial Challenges and the Subjective Well‑being of First‑year Students at a Comprehensive South African University. J Stud Aff Afr [Internet]. 2020 [cited 2025 Apr 2]; 8(1). Available from:
[32] Mann M, Hosman CMH, Schaalma HP, de Vries NK. Self-esteem in a broad-spectrum approach for mental health promotion. Health Educ Res. 2004 Aug; 19(4): 357–72.
[33] Gross JJ, John OP. Individual differences in two emotion regulation processes: implications for affect, relationships, and well-being. J Pers Soc Psychol. 2003 Aug; 85(2): 348–62.
[34] Gerber M, Pühse U. Review article: do exercise and fitness protect against stress-induced health complaints? A review of the literature. Scand J Public Health. 2009 Nov; 37(8): 801–19.
[35] (PDF) Relationship between Psychosocial Factors and Physical Activity among Undergraduate Students from a South African University. ResearchGate [Internet]. 2025 Jan 7 [cited 2025 Apr 2]; Available from:
[36] Cacioppo JT, Cacioppo S. The growing problem of loneliness. Lancet Lond Engl. 2018 Feb 3; 391(10119): 426.
[37] Coelho J, Montagni I, Micoulaud-Franchi JA, Philip P, Arsandaux J, Tzourio C. Étude du sommeil chez des étudiants et relation longitudinale avec symptômes anxieux et dépressifs. Médecine Sommeil. 2021 Mar 1; 18(1): 38.
[38] Bi C, Lin H, Zhang J, Zhao Z. Association between Sleep Quality and Depression Symptoms in Chinese College Students during the COVID-19 Lockdown Period. Children. 2022 Aug; 9(8): 1237.
[39] Richardson T, Elliott P, Roberts R. The relationship between personal unsecured debt and mental and physical health: a systematic review and meta-analysis. Clin Psychol Rev. 2013 Dec; 33(8): 1148–62.
[40] Eisenberg D, Gollust SE, Golberstein E, Hefner JL. Prevalence and correlates of depression, anxiety, and suicidality among university students. Am J Orthopsychiatry. 2007 Oct; 77(4): 534–42.
[41] Hunt J, Eisenberg D. Mental health problems and help-seeking behavior among college students. J Adolesc Health Off Publ Soc Adolesc Med. 2010 Jan; 46(1): 3–10.
[42] Santini ZI, Koyanagi A, Tyrovolas S, Mason C, Haro JM. The association between social relationships and depression: a systematic review. J Affect Disord. 2015 Apr 1; 175: 53–65.
[43] Wu D, Liu F, Huang S. Assessment of the relationship between living alone and the risk of depression based on longitudinal studies: A systematic review and meta-analysis. Front Psychiatry. 2022; 13: 954857.
[44] Lassale C, Batty GD, Baghdadli A, Jacka F, Sánchez-Villegas A, Kivimäki M, et al. Healthy dietary indices and risk of depressive outcomes: a systematic review and meta-analysis of observational studies. Mol Psychiatry. 2019 Jul; 24(7): 965–86.
[45] Jacka FN, Kremer PJ, Leslie ER, Berk M, Patton GC, Toumbourou JW, et al. Associations between diet quality and depressed mood in adolescents: results from the Australian Healthy Neighbourhoods Study. Aust N Z J Psychiatry. 2010 May; 44(5): 435–42.
[46] Sowislo JF, Orth U. Does low self-esteem predict depression and anxiety? A meta-analysis of longitudinal studies. Psychol Bull. 2013 Jan; 139(1): 213–40.
[47] Sargent JT, Crocker J, Luhtanen RK. Contingencies of Self–Worth and Depressive Symptoms in College Students. J Soc Clin Psychol. 2006 Jun; 25(6): 628–46.
[48] Kupferberg A, Hasler G. The social cost of depression: Investigating the impact of impaired social emotion regulation, social cognition, and interpersonal behavior on social functioning. J Affect Disord Rep. 2023 Dec 1; 14: 100631.
[49] Carver CS, Connor-Smith J. Personality and coping. Annu Rev Psychol. 2010; 61: 679–704.
[50] Compas BE, Jaser SS, Bettis AH, Watson KH, Gruhn MA, Dunbar JP, et al. Coping, emotion regulation, and psychopathology in childhood and adolescence: A meta-analysis and narrative review. Psychol Bull. 2017 Sep; 143(9): 939–91.
[51] Holahan CJ, Moos RH. Personal and contextual determinants of coping strategies. J Pers Soc Psychol. 1987 May; 52(5): 946–55.
Cite This Article
  • APA Style

    Namndiro, G. P. O., Tine, J. A. D., Sow, A., Seck, I. (2025). Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal. Central African Journal of Public Health, 11(3), 113-134. https://doi.org/10.11648/j.cajph.20251103.13

    Copy | Download

    ACS Style

    Namndiro, G. P. O.; Tine, J. A. D.; Sow, A.; Seck, I. Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal. Cent. Afr. J. Public Health 2025, 11(3), 113-134. doi: 10.11648/j.cajph.20251103.13

    Copy | Download

    AMA Style

    Namndiro GPO, Tine JAD, Sow A, Seck I. Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal. Cent Afr J Public Health. 2025;11(3):113-134. doi: 10.11648/j.cajph.20251103.13

    Copy | Download

  • @article{10.11648/j.cajph.20251103.13,
      author = {Gad Papin Oholiab Namndiro and Jean Augustin Diégane Tine and Abdourahmane Sow and Ibrahima Seck},
      title = {Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal
    },
      journal = {Central African Journal of Public Health},
      volume = {11},
      number = {3},
      pages = {113-134},
      doi = {10.11648/j.cajph.20251103.13},
      url = {https://doi.org/10.11648/j.cajph.20251103.13},
      eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.cajph.20251103.13},
      abstract = {Mental health among students in Senegal remains an under-explored area, with limited research and prevention efforts. At the African Center for Higher Studies in Management (CESAG), students face high academic demands, highlighting the importance of investigating stress, anxiety, and depression within this population. This study aimed to identify factors associated with anxiety-depressive states, specifically stress, anxiety and depression, among CESAG students. A cross-sectional, observational, descriptive, and analytical study was conducted from July 22 to August 23, 2024. Data were collected through an electronic questionnaire. Stress, anxiety, and depression were assessed using the Perceived Stress Scale (PSS), the Generalized Anxiety Disorder-7 (GAD-7) score, and the Patient Health Questionnaire-9 (PHQ-9) score, respectively. Data analysis was performed using RStudio (version 2024.12.1.563). Informed and voluntary consent of the participants was ensured. A total of 426 students completed the online questionnaire. The mean age was 23.4 years. Stress was observed in 45.6% of students, anxiety in 21.4%, and depression in 35.4%. Risk factors for stress included belonging to the [20-25 years[ age group (ORa = 5.68, 95%CI [1.67-19.31]) or the ≥30 years group (ORa = 8.8, 95%CI [1.5-51.64]), poor sleep quality (ORa = 7.05, 95%CI [2.32-21.44]), low financial income (ORa = 11.23, 95%CI [4.34-29.06]), low self-esteem (ORa = 15.13, 95%CI [3.18-72.13]) or moderate self-esteem (ORa = 7.96, 95%CI [2.83-22.4]), a negative emotional state (ORa = 4.7, 95%CI [1.64-13.46]), and the absence of physical activity (ORa = 5.03, 95%CI [1.88-13.49]). Living alone was a protective factor against anxiety among students (ORa = 0.16, 95%CI [0.09-0.29]). Depression was associated with several risk factors: poor sleep quality (ORa = 8.07, 95%CI [2.72-23.88]), low financial income (ORa = 4.38, 95%CI [1.42-13.48]), living alone (ORa = 3.53, 95%CI [1.1-11.34]), poor diet (ORa = 13.03, 95%CI [3.84-44.18]), low self-esteem (ORa = 18.21; 95%CI [2.62-126.41]) or moderate self-esteem (ORa = 9.19, 95%CI [1.66-51.01]), and a negative emotional state (ORa = 5.54, 95%CI [1.64-18.71]). A passive coping style was found to be protective (ORa = 0.25, 95%CI [0.08-0.8]). These findings emphasize the importance of preventive strategies to promote CESAG students’ mental health and well-being. Targeted awareness campaigns and psychological support are essential to achieving this goal.
    },
     year = {2025}
    }
    

    Copy | Download

  • TY  - JOUR
    T1  - Factors Associated with Stress, Anxiety, and Depression Among Management School Students in Senegal
    
    AU  - Gad Papin Oholiab Namndiro
    AU  - Jean Augustin Diégane Tine
    AU  - Abdourahmane Sow
    AU  - Ibrahima Seck
    Y1  - 2025/06/18
    PY  - 2025
    N1  - https://doi.org/10.11648/j.cajph.20251103.13
    DO  - 10.11648/j.cajph.20251103.13
    T2  - Central African Journal of Public Health
    JF  - Central African Journal of Public Health
    JO  - Central African Journal of Public Health
    SP  - 113
    EP  - 134
    PB  - Science Publishing Group
    SN  - 2575-5781
    UR  - https://doi.org/10.11648/j.cajph.20251103.13
    AB  - Mental health among students in Senegal remains an under-explored area, with limited research and prevention efforts. At the African Center for Higher Studies in Management (CESAG), students face high academic demands, highlighting the importance of investigating stress, anxiety, and depression within this population. This study aimed to identify factors associated with anxiety-depressive states, specifically stress, anxiety and depression, among CESAG students. A cross-sectional, observational, descriptive, and analytical study was conducted from July 22 to August 23, 2024. Data were collected through an electronic questionnaire. Stress, anxiety, and depression were assessed using the Perceived Stress Scale (PSS), the Generalized Anxiety Disorder-7 (GAD-7) score, and the Patient Health Questionnaire-9 (PHQ-9) score, respectively. Data analysis was performed using RStudio (version 2024.12.1.563). Informed and voluntary consent of the participants was ensured. A total of 426 students completed the online questionnaire. The mean age was 23.4 years. Stress was observed in 45.6% of students, anxiety in 21.4%, and depression in 35.4%. Risk factors for stress included belonging to the [20-25 years[ age group (ORa = 5.68, 95%CI [1.67-19.31]) or the ≥30 years group (ORa = 8.8, 95%CI [1.5-51.64]), poor sleep quality (ORa = 7.05, 95%CI [2.32-21.44]), low financial income (ORa = 11.23, 95%CI [4.34-29.06]), low self-esteem (ORa = 15.13, 95%CI [3.18-72.13]) or moderate self-esteem (ORa = 7.96, 95%CI [2.83-22.4]), a negative emotional state (ORa = 4.7, 95%CI [1.64-13.46]), and the absence of physical activity (ORa = 5.03, 95%CI [1.88-13.49]). Living alone was a protective factor against anxiety among students (ORa = 0.16, 95%CI [0.09-0.29]). Depression was associated with several risk factors: poor sleep quality (ORa = 8.07, 95%CI [2.72-23.88]), low financial income (ORa = 4.38, 95%CI [1.42-13.48]), living alone (ORa = 3.53, 95%CI [1.1-11.34]), poor diet (ORa = 13.03, 95%CI [3.84-44.18]), low self-esteem (ORa = 18.21; 95%CI [2.62-126.41]) or moderate self-esteem (ORa = 9.19, 95%CI [1.66-51.01]), and a negative emotional state (ORa = 5.54, 95%CI [1.64-18.71]). A passive coping style was found to be protective (ORa = 0.25, 95%CI [0.08-0.8]). These findings emphasize the importance of preventive strategies to promote CESAG students’ mental health and well-being. Targeted awareness campaigns and psychological support are essential to achieving this goal.
    
    VL  - 11
    IS  - 3
    ER  - 

    Copy | Download

Author Information
  • Management of Companies and other Organizations, African Center for Higher Studies in Management (CESAG), Dakar, Senegal; Institute of Health and Development (ISED), Faculty of Medicine, Pharmacy, and Dentistry (FMPO), Cheikh Anta DIOP University (UCAD), Dakar, Senegal

    Biography: Gad Papin Oholiab Namndiro is a trained medical doctor, epide-miologist, and currently a PhD student in epidemiology. He holds degrees from the Institute of Health and Development (ISED) at Cheikh Anta Diop University in Dakar and from the African Center for Higher Studies in Management (CESAG), where he received specialized training in the evaluation of projects, programs, and pub-lic policies. His background combines strong medical expertise with solid skills in public health and evaluation, placing him at the inter-section of medical sciences, epidemiological research, and health policy analysis.

    Research Fields: Epidemiology, adolescent health, clinical aspects related to health, emerging infectious diseases, One Health, antimicrobial resistance, etc.

  • Institute of Health and Development (ISED), Faculty of Medicine, Pharmacy, and Dentistry (FMPO), Cheikh Anta DIOP University (UCAD), Dakar, Senegal; Mental Health Department (DSM), Ministry of Health and Social Action (MSAS), Dakar, Senegal

    Biography: Jean Augustin Diégane Tine is a psychiatrist and epidemiologist. He serves as a Professor of Public Health at Cheikh Anta Diop Uni-versity in Dakar and heads the Mental Health Department at the Ministry of Health and Social Action in Senegal. He has authored numerous scientific publications on mental health and public health. His academic and institutional commitment has made him a leading figure in the fields of mental health and epidemiology in Senegal and West Africa.

    Research Fields: Epidemiology, mental health, public health, adolescent health, clinical aspects related to health, community health, health policy and plan-ning, health promotion, nutrition and health, pediatrics and child health, rural health, school health, sexual and reproductive health, etc.

  • Institute of Health and Development (ISED), Faculty of Medicine, Pharmacy, and Dentistry (FMPO), Cheikh Anta DIOP University (UCAD), Dakar, Senegal; Public Health Department (DSP), Pasteur Institute of Dakar (IPD), Dakar, Senegal

    Biography: Abdourahmane Sow, a medical doctor and holder of a PhD in public health, currently serves as the Director of the Department of Public Health at the Pasteur Institute of Dakar. He also holds a prominent position as an academic researcher at the Cheikh Anta Diop University of Dakar (UCAD). With a distinguished profes-sional background, he has assumed leading roles within the Senega-lese health system and in the West African sub-region. In this capaci-ty, he is a key figure in managing public health crises and events, contributing with discernment and rigor to the development and implementation of large-scale health management strategies.

    Research Fields: Epidemiology, public health, emerging infectious diseases, arbo-viruses, clinical aspects related to health, community health, health policy and planning, health promotion, nutrition and health, rural health, etc.

  • Institute of Health and Development (ISED), Faculty of Medicine, Pharmacy, and Dentistry (FMPO), Cheikh Anta DIOP University (UCAD), Dakar, Senegal

    Biography: Ibrahima Seck is a prominent figure in public health in Senegal. He is a Full Professor of Public Health at Cheikh Anta Diop University in Dakar (UCAD), where he also serves as Director of the Institute of Health and Development (ISED) and Head of the Preventive Medicine Department at the Faculty of Medicine, Pharmacy, and Dentistry. He has held several key positions in the Senegalese health sector and has authored numerous scientific publications in public health. His exceptional career and sustained commitment make him a leading authority in his field.

    Research Fields: Epidemiology, public health, adolescent health, allied health sciences, clinical aspects related to health, community health, environmental health, health policy and planning, health promotion, nutrition and health, pediatrics and child health, rural health, school health, sexual and reproductive health, medicine and health, urban health and women's health, etc.